
Connect with Us


How Advancements in Arthritis Care Are Changing Patient Treatment

The approach to treating joint pain and systemic inflammation looks completely different today than it did five years ago. Rheumatologists previously relied on heavy corticosteroids and eventual joint replacement surgeries to manage severe osteoarthritis and rheumatoid arthritis. Medical researchers now focus directly on structural tissue regeneration and precise immune system regulation. These clinical upgrades stop joint degradation at its biological source rather than just masking the daily pain.
Patients facing an arthritis diagnosis must learn how these new medical options function. From implanted nerve stimulators to bio-engineered cartilage, the treatment options available in 2026 offer aggressive disease modification. The high retail cost of these interventions forces insurance companies to adjust their coverage policies. Reviewing the latest clinical breakthroughs helps patients plan their medical care and secure the financial support required to access top-tier therapies.
Regenerating Joint Cartilage Without Surgery
Medical science historically viewed cartilage loss as a permanent condition. A patient with bone-on-bone osteoarthritis simply waited until the pain justified a total knee replacement. New regenerative therapies dismantle this assumption completely. The federal Advanced Research Projects Agency for Health recently launched the NITRO program, which funds injectable treatments that force the human body to regrow its own articular cartilage.
Researchers identified specific aging proteins that prevent tissue repair. By blocking these proteins, experimental medications prompt aging cells to generate fresh cartilage and bone. Clinical testing shows these targeted injectables reverse osteoarthritis damage without requiring invasive orthopedic surgery. These joint-sparing treatments drastically lower facility fees and eliminate lengthy physical rehabilitation. Recognizing that early detection improves treatment outcomes allows patients to seek these regenerative injections before joint destruction becomes irreversible.
Neuromodulation And Bioelectronic Implants
Treating autoimmune forms of the disease, like rheumatoid arthritis, requires suppressing the overactive immune response. Pharmaceutical drugs often cause severe systemic side effects, leaving patients vulnerable to infections. Bioelectronic medicine offers an entirely different delivery mechanism. The FDA recently approved miniaturized devices that attach directly to the vagus nerve in the neck.
A surgeon implants the small device during a brief outpatient procedure. The implant sends calibrated electrical pulses to the brain, activating the body’s natural cholinergic anti-inflammatory pathway. This electrical signal tells the spleen to stop producing the specific cytokines that attack healthy joint tissue. The Arthritis Foundation reports that neurostimulation provides deep symptom relief for patients who fail to respond to standard biologic injections. Securing insurance approval for this hardware demands precise clinical documentation. Carriers frequently use AI health insurance assistants to review these surgical requests, checking if the patient exhausted all traditional medication options first.
Targeted Biologics And Precision Medicine
The pharmaceutical pipeline for inflammatory arthritis now favors highly targeted molecular interventions. Older biologic drugs suppressed large sections of the immune system. The latest iterations use nanobodies—proteins significantly smaller than traditional antibodies. These tiny molecules penetrate dense joint tissue more effectively to block specific inflammatory pathways.
Doctors combine these advanced biologics with detailed biomarker testing to predict exactly which drug will clear a patient’s symptoms. This precision medicine model eliminates the painful trial-and-error phase of rheumatology. For the most severe, refractory cases, oncologists and rheumatologists now test CAR-T cell therapy. This treatment reprograms the patient’s own T-cells to hunt and destroy the malfunctioning B-cells causing the autoimmune attack. The National Institutes of Health monitors these aggressive cellular therapies as they move through clinical trials.
Minimally Invasive Relief For Knee Osteoarthritis
Patients who do not qualify for cartilage regeneration still have access to new non-surgical pain management tools. Genicular Artery Embolization blocks abnormal blood flow to the inflamed lining of the knee, reducing swelling and stiffness instantly. Water-cooled radiofrequency ablation safely deactivates the specific sensory nerves transmitting knee pain to the brain, providing relief that lasts for months.
High-platelet plasma injections show superior clinical efficacy compared to older synthetic lubricants. These outpatient procedures keep older adults active and mobile. Retirees evaluating the cheapest $0 premium Medicare Advantage plans must check the coverage limits for outpatient orthopedic procedures. Some private Medicare plans categorize these specific nerve blocks and embolizations as experimental, leaving the patient responsible for the entire clinic bill.

Managing Insurance Coverage For Advanced Therapies
Modern arthritis treatments carry massive list prices. A single year of a targeted nanobody biologic or a vagus nerve implant costs tens of thousands of dollars. Insurance carriers protect their profit margins by enforcing strict step-therapy protocols. They force the patient to try cheaper, older medications before authorizing the newer interventions.
You must build a flawless paper trail with your rheumatologist to bypass these corporate restrictions. Submit detailed medical records proving that conventional pills failed to stop your joint degradation. Researching the top-rated health insurance companies before open enrollment guarantees you select a carrier with an updated specialty drug formulary. The Centers for Medicare & Medicaid Services updates its coverage rules annually, setting the baseline for what private carriers must approve. Matching your insurance policy to your specific joint health needs prevents these medical breakthroughs from causing financial ruin.
Arthritis Treatment Upgrades At A Glance
| Treatment Type | Clinical Mechanism | Direct Impact On Patients |
| Cartilage Regeneration | Blocks aging proteins to regrow healthy joint tissue | Prevents the need for total knee or hip replacement surgeries |
| Vagus Nerve Stimulation | Uses an implant to send electrical pulses to the brain | Stops rheumatoid inflammation without systemic pharmaceutical side effects |
| Nanobody Biologics | Delivers tiny targeted proteins deep into dense joints | Provides faster symptom relief for patients failing standard medications |
| Genicular Artery Embolization | Blocks abnormal blood flow to the inflamed knee lining | Reduces chronic osteoarthritis pain through a simple outpatient procedure |
Latest Rheumatoid Arthritis Breakthroughs for 2026
This video provides an excellent breakdown of the newest targeted biologics, FDA-approved bioelectronic implants, and precision medicine strategies reshaping autoimmune joint care this year.
How Health Insurance Handles Stem Cells and Medical Treatment

Regenerative medicine promises to change how doctors treat severe illnesses. Researchers study how human cells repair damaged tissues, offering hope for patients with chronic joint pain, autoimmune disorders, and degenerative nerve diseases. Despite these clinical advancements, paying for stem cells and medical treatment remains a massive hurdle for the average consumer. The American health insurance system approaches cellular therapies with extreme caution. Carriers view most of these modern interventions as highly experimental. They refuse to pay for treatments that lack decades of verified safety data.
Patients seeking these therapies frequently face a harsh financial reality. A clinic might offer a new injection to cure a torn rotator cuff, but the insurance company will deny the claim instantly. Securing financial coverage requires a clear strategy. You must know exactly which specific cellular products the federal government approves and how corporate carriers code those procedures. Patients who learn these billing rules protect their household budgets from devastating out-of-pocket medical debt.
The Strict Federal Approval Process
The government strictly regulates how doctors harvest and inject human cells. As we move through 2026, the Food and Drug Administration maintains a very narrow list of authorized cellular therapies. The agency primarily approves hematopoietic stem cells derived from bone marrow or umbilical cord blood. Doctors use these specific cells to treat severe blood disorders and aggressive cancers like leukemia and lymphoma.
If a clinic offers cellular injections for knee arthritis or multiple sclerosis, the government classifies that procedure as an off-label or experimental use. Health insurance carriers build their entire coverage framework around these federal decisions. Reviewing the official list of FDA approved cellular and gene therapy products shows exactly where commercial insurance draws the line. Carriers gladly pay for a bone marrow transplant to cure cancer, because clinical data proves that early detection improves treatment outcomes for these specific diseases. They flatly deny claims for off-label joint injections.
What Commercial Policies And Medicare Cover
When a doctor prescribes an approved cellular transplant for a blood cancer, insurance policies generally cover the massive hospital bills. Medicare Part A pays for the inpatient hospital stay, while Part B covers the outpatient medical services, doctor visits, and continuous monitoring. Commercial insurance companies follow this exact same standard. They cover the costly process of testing donors, matching human leukocyte antigens, and harvesting the bone marrow.
Securing this coverage requires strict adherence to corporate network rules. Most major carriers force patients to undergo these complex procedures at designated Centers of Excellence. These specific hospitals meet rigorous clinical standards set by the insurer. Seeking treatment at an out-of-network facility results in immediate claim denials. As consumers evaluate the top-rated health insurance companies during open enrollment, they must verify which local hospital systems hold this specialized transplant certification. The American Cancer Society provides extensive resources helping patients appeal wrongful denials when carriers reject life-saving transplant claims.
The Financial Burden Of Cash-Pay Clinics
A massive secondary market exists outside of standard hospital systems. Independent regenerative clinics offer unapproved cellular injections for joint pain, aging, and chronic fatigue. Because insurance companies label these applications as experimental, the patient bears the entire financial burden. The cost of a single orthopedic cellular injection ranges from five thousand to twenty-five thousand dollars depending on the extraction method.
These clinics require upfront cash payments. They do not bill your insurance provider. This unregulated cash-pay market operates outside standard medical billing structures, contributing heavily to the crisis of why healthcare costs keep rising for the American public. Patients frequently empty their savings accounts to fund these unproven treatments. The Federal Trade Commission actively investigates clinics that make false guarantees regarding clinical outcomes without proper scientific backing. You must demand written proof of clinical success rates before handing a cash deposit to a private regenerative center.
Strategies For Managing Treatment Approvals
Patients prescribed a legitimate, approved transplant must manage the billing process aggressively. Your hospital’s financial coordinator handles the initial prior authorization, but you must monitor the paperwork constantly. Insurance companies frequently deny initial claims due to simple coding errors. A missing diagnostic code will trigger an automated rejection letter.
You maintain the legal right to file an appeal. Force your medical team to submit peer-reviewed clinical data proving the treatment meets standard medical necessity guidelines. Keep detailed records of every phone call with your insurance representative. Cellular therapies save lives, but they carry astronomical list prices. Staying organized and demanding exact coverage details in writing guarantees you receive the care you need without facing permanent financial ruin.
Cellular Therapy Coverage At A Glance
| Treatment Type | FDA Status | Insurance Coverage Expectation |
| Bone Marrow Transplants | Fully Approved for specific cancers | Covered, but requires treatment at a Center of Excellence |
| Cord Blood Hematopoietic Cells | Fully Approved for blood disorders | Covered under standard major medical and Medicare policies |
| Orthopedic Joint Injections | Considered Experimental | Denied by insurers; requires high out-of-pocket cash payments |
| Anti-Aging Cellular IVs | Unapproved and unregulated | Denied entirely; patients assume all financial and clinical risk |
Advanced Cardiac Care Techniques: Structural Repairs & Imaging
Heart disease treatments undergo constant refinement. Medical researchers develop less invasive methods to fix structural defects inside the heart. Advanced imaging software gives doctors a perfect view of the cardiovascular system. These clinical upgrades translate directly into better survival rates for patients facing severe cardiac episodes. Modern medicine keeps patients alive longer.
The financial side of this equation presents a different challenge. The tools required to fix a failing heart cost a premium. Insurance companies evaluate every new scanner and surgical technique to control their corporate spending. Patients facing a cardiac diagnosis must learn how their insurance policy handles these modern interventions. Knowing the rules of the medical billing system prevents a life-saving surgery from causing personal bankruptcy.
The Shift To Minimally Invasive Structural Repairs
Structural heart disease affects the valves, walls, and chambers of the heart. Historically, fixing a leaky valve meant cracking the chest open and placing the patient on a bypass machine. Today, cardiologists perform structural heart repairs using long, flexible catheters. They thread tiny devices through blood vessels in the groin or wrist directly to the heart. This approach allows doctors to replace or repair damaged tissues without subjecting the patient to major surgical trauma.
Transcatheter Edge-to-Edge Repair (TEER) represents a prime example. This procedure fixes the mitral valve using a small clip. The American College of Cardiology tracks the success rates of these catheter-based interventions, showing steep drops in hospital mortality. Shorter hospital stays save money in theory. The specialized clips and artificial valves cost thousands of dollars to manufacture. Seniors needing these specific valve repairs should compare the cheapest $0 premium Medicare Advantage plans to confirm their chosen network includes hospitals equipped for structural cardiology.
Advanced Imaging Drives Surgical Precision
Surgeons cannot fix what they cannot see clearly. Advanced cardiac imaging replaces older, flat X-rays with dynamic, three-dimensional models. Cardiac MRI and 3D echocardiography allow doctors to view the heart beating in real time from every conceivable angle. These tools identify microscopic tears in heart valves before the patient ever enters the operating room.
Doctors use these images to plan structural repairs down to the millimeter. They print 3D physical models of a patient’s heart to practice the surgery beforehand. The Radiological Society of North America confirms that highly detailed preoperative imaging directly reduces the time a patient spends under anesthesia. Insurance companies demand proof that these expensive scans possess direct medical necessity. Carriers deploy AI health insurance assistants to review imaging requests. These algorithms check the patient’s medical history against standard clinical guidelines before granting approval.
How Insurers Evaluate Expensive Cardiac Procedures
Bringing new cardiac technologies to the market forces insurers to adapt their billing rules. Medical directors at major insurance firms review clinical trial data before adding a new structural repair technique to their covered benefits list. A carrier labels a procedure experimental and denies the claim outright if it lacks long-term data.
Patients face strict prior authorization requirements for advanced imaging and catheter surgeries. The Centers for Medicare & Medicaid Services sets the baseline for what private insurers cover. Commercial carriers usually follow suit the moment Medicare approves a new valve replacement. Consumers must verify their coverage details annually. Selecting the right policy from top-rated health insurance companies protects patients from sudden denials when they need life-saving cardiac interventions. Active engagement with an insurance representative confirms which specific heart centers fall inside the preferred network.
Protecting Your Finances During Treatment
State-of-the-art heart care drives up hospital facility fees. Medical centers spend millions purchasing 3D imaging machines and outfitting specialized hybrid operating rooms. They pass these expenses straight to the consumer. High out-of-pocket maximums leave patients vulnerable to severe medical debt following a heart procedure.
Independent health economists continuously study rising healthcare costs and point directly to specialty surgical centers as a primary factor. Patients must ask their cardiologists for exact billing codes before scheduling a procedure. Cross-referencing those codes with an insurance representative prevents surprise bills. Seeking a second opinion at an in-network facility keeps financial exposure strictly limited.
Advanced Cardiac Care At A Glance
| Procedure / Technology | How It Functions | Direct Patient Impact |
| Structural Heart Repair | Replaces or fixes heart valves using tiny catheters | Lowers surgical risk and shortens recovery times |
| 3D Echocardiography | Creates live three-dimensional models of the beating heart | Allows surgeons to plan repairs with extreme precision |
| Cardiac MRI | Scans the heart for tissue damage and blood flow issues | Identifies hidden defects before symptoms appear |
| Prior Authorization | Insurers review clinical data before approving the surgery | Forces patients to prove medical need to secure coverage |
How Modern Treatments Improve Heart Disease Survival Rates
Heart disease remains a leading cause of mortality in the United States. Medical science continues to introduce new interventions. These clinical upgrades directly improve heart disease survival rates. Patients face shorter hospital stays. They experience fewer surgical complications. Medical bills look very different today compared to a decade ago.
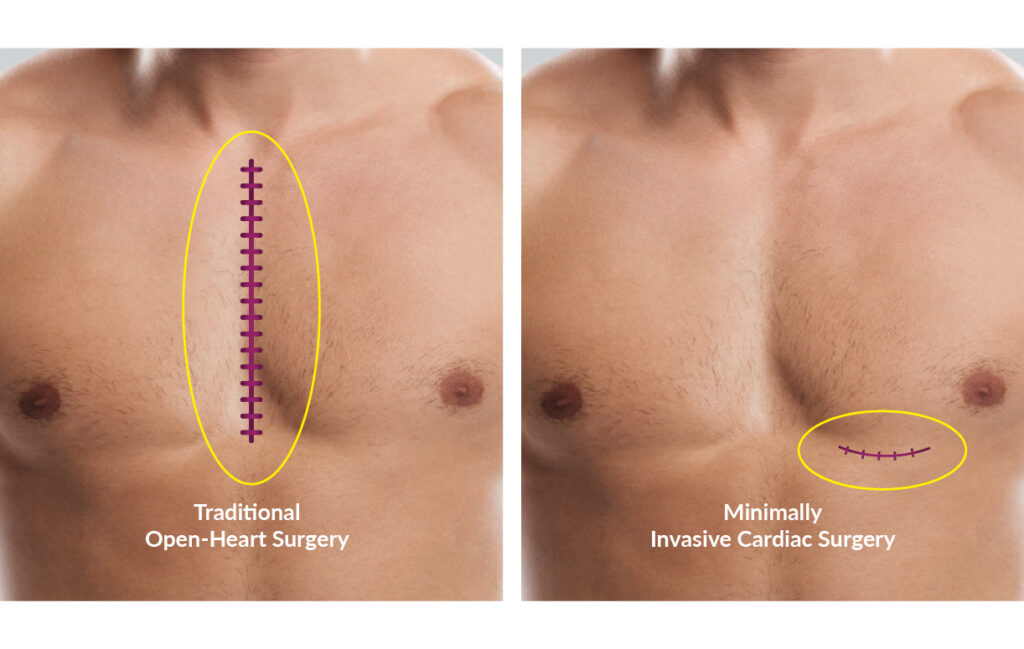
Open-heart surgery used to be the default standard for severe cardiac blockages. Today, cardiologists favor minimally invasive techniques. Pharmaceutical researchers develop targeted biologics to manage cholesterol. Technology companies build digital monitors to track arrhythmias from the patient’s living room. These combined efforts keep patients alive longer. Navigating the cost of these interventions requires a strategic approach to health insurance. Medical innovation carries a high price tag. Patients must align their insurance policies with the exact type of care they need to avoid devastating hospital bills.
The Shift To Minimally Invasive Cardiac Care
Surgeons now repair major structural defects without opening a patient’s chest. Transcatheter Aortic Valve Replacement (TAVR) replaces a damaged valve through a small catheter. The surgeon makes a tiny incision in the leg and guides the new valve up to the heart. This approach spares the patient from a massive physical trauma. Recovery time drops from several months to just a few weeks.
The American Heart Association reports exceptionally high success rates for these catheter-based procedures. Older adults see the largest benefit from these less aggressive surgeries. Traditional open-heart surgery carries severe risks for seniors. Minimally invasive options give elderly patients a viable path to recovery. High facility fees accompany these advanced operating rooms. Exploring the cheapest $0 premium Medicare Advantage plans helps seniors secure coverage for these expensive hospital stays without increasing their fixed monthly expenses.
Advanced Medications Target High Cholesterol
Pharmaceutical interventions look completely different today. Statins dominated the cardiovascular market for years. Many patients could not tolerate the muscle aches associated with standard statin therapy. Doctors now prescribe PCSK9 inhibitors for patients with stubborn cholesterol levels. These injectable biologics force the liver to clear low-density lipoprotein from the blood stream. They lower bad cholesterol numbers far beyond the limits of traditional pills.
The Centers for Disease Control and Prevention tracks how maintaining low cholesterol prevents secondary heart attacks. Stopping a second heart attack dramatically raises long-term survival statistics. Drug makers charge thousands of dollars for these specific biologic injections. Looking closely at how pharmaceutical companies influence drug pricing explains the high pharmacy counter receipts. Patients must check their insurance formularies closely. Carriers frequently require strict prior authorizations before they agree to cover these expensive monthly injections.
Continuous Heart Monitoring Inside The Home
Medical care extends past the hospital discharge date. Doctors monitor heart rhythms from afar. Small digital implants track arrhythmias and send alerts directly to the clinic. Wearable smartwatches detect signs of atrial fibrillation. Catching a minor flutter early prevents a massive stroke later. Continuous data gives cardiologists a clear picture of the patient’s daily heart function.
The Food and Drug Administration regulates these continuous monitoring tools to guarantee clinical accuracy. Insurers embrace this preventive technology. Catching problems early keeps patients out of expensive emergency rooms. Corporate carriers use AI health insurance assistants to process the constant stream of diagnostic data. Algorithms flag dangerous heart rate trends and alert the medical team automatically. These digital safety nets give patients confidence during their recovery process.
Managing The Financial Reality Of Cardiac Care
Financial strategy determines access to these medical upgrades. State-of-the-art procedures carry massive list prices. Hospital billing departments code minimally invasive surgeries aggressively. An insurance carrier might deny a new surgical technique if the medical director deems it experimental. Patients must review their network directories before scheduling any operation. Out-of-network facility fees can easily bankrupt a family.
The Centers for Medicare & Medicaid Services outlines strict rules for cardiac rehabilitation reimbursement. Insurers follow these federal guidelines closely. Securing proper care means engaging directly with your benefits administrator. You must demand clear explanations of your out-of-pocket maximums. Reviewing the top-rated health insurance companies ensures your policy covers modern interventions. Matching your coverage to your exact medical needs is the most effective way to protect your physical and financial health.
Heart Disease Interventions At A Glance
| Treatment Type | How It Functions | Direct Patient Benefit |
| Catheter Surgeries | Replaces valves through a small leg incision | Lowers surgical risk and speeds up recovery times |
| PCSK9 Inhibitors | Injected biologics clear bad cholesterol from the blood | Prevents secondary heart attacks in high-risk patients |
| Digital Implants | Transmits heart rhythm data directly to the doctor | Detects dangerous arrhythmias before a stroke occurs |
| Cardiac Rehab | Supervised exercise and diet management programs | Strengthens the heart muscle after a major cardiac event |
The Evolution of Dementia Treatment Over the Past 20 Years

For decades, an Alzheimer’s or dementia diagnosis was accompanied by a devastating reality: the medical community had no way to slow the progression of the disease. Historically, dementia treatment was limited to prescribing medications that offered, at best, a temporary reprieve from cognitive decline. However, the last 20 years have witnessed a profound scientific revolution in the field of neurodegenerative disease. After enduring decades of failed clinical trials, researchers have successfully transitioned from merely masking the symptoms of the condition to actively altering the underlying biological course of the illness.
Today, as we navigate 2026, this scientific evolution is reshaping the American healthcare landscape. The introduction of highly complex, targeted biologics has completely transformed patient expectations, but it has also triggered a massive financial challenge for the insurance industry and government payers. Understanding how dementia care has evolved is essential for patients and caregivers who must now navigate a maze of high-cost infusions, complex diagnostic requirements, and rigorous insurance registries to access the latest medical breakthroughs.
The Era Of Symptom Management
In the early 2000s, the pharmaceutical arsenal against Alzheimer’s disease was incredibly limited. The standard of care relied heavily on cholinesterase inhibitors and NMDA receptor antagonists. These oral medications were designed to regulate the chemical messengers in the brain that transmit electrical signals, temporarily improving memory, mood, and daily functioning for a subset of patients.
While these drugs provided meaningful short-term relief, they did not address the root cause of the neurological decay. The disease continued to relentlessly ravage the brain’s physical structure underneath the chemical patch. During this era, the pharmaceutical industry poured billions of dollars into research and development, launching dozens of high-profile clinical trials aimed at stopping the disease, only to watch compound after compound fail in late-stage testing. This prolonged period of clinical stagnation left millions of families relying entirely on supportive care and long-term nursing facilities.
The Breakthrough Of Monoclonal Antibodies
The turning point in the evolution of dementia treatment arrived when researchers finally succeeded in targeting the toxic proteins that accumulate in the brains of Alzheimer’s patients. The scientific consensus coalesced around the “amyloid hypothesis,” which posits that clearing the sticky beta-amyloid plaques from the brain can slow the rate of cognitive decline.
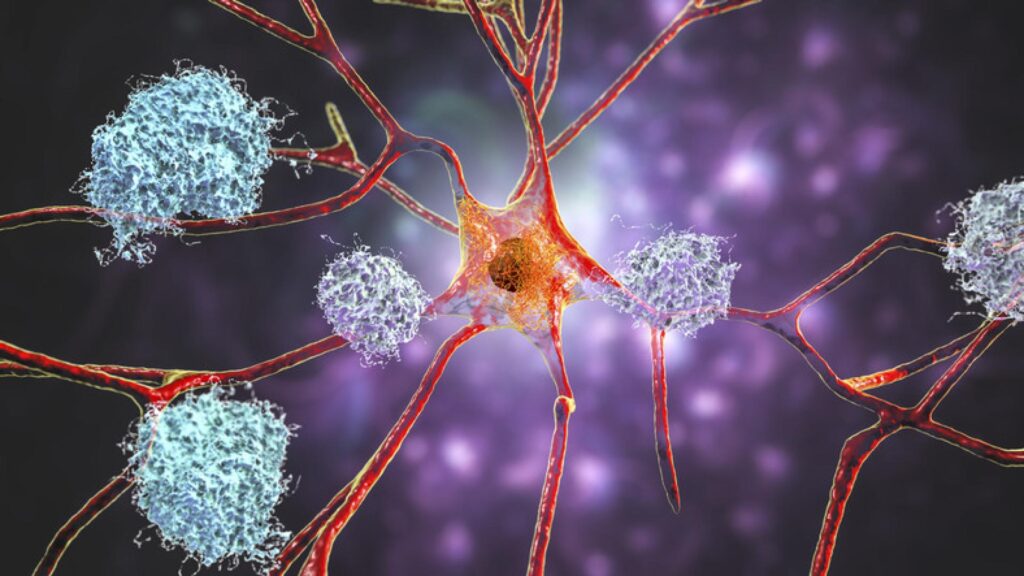
This led to the recent and rapid approval of a new class of drugs known as monoclonal antibodies, including breakthrough therapies like lecanemab and donanemab. Unlike the daily pills of the past, these therapies are engineered antibodies administered via intravenous infusion. They physically bind to and remove the amyloid plaques, representing the first time in history that medications have been proven to slow the clinical progression of early-stage Alzheimer’s disease. For patients, this translates into preserving their independence and cognitive function for valuable additional months or even years.
How Modern Diagnostics Changed The Landscape
The arrival of disease-modifying therapies fundamentally changed how dementia is diagnosed. Because monoclonal antibodies are only effective in the early stages of Alzheimer’s and specifically target amyloid proteins, physicians can no longer rely on cognitive tests alone to prescribe treatment. A definitive biological diagnosis is now a strict medical and financial requirement.
To confirm the presence of amyloid plaques, patients must undergo advanced biomarker testing. Historically, this required an expensive brain PET scan or an invasive lumbar puncture. However, recent advancements have introduced highly accurate blood tests capable of detecting these microscopic proteins, dramatically improving access to early diagnosis. As we have seen across modern medicine, securing favorable early detection treatment outcomes is the most critical factor in determining whether a patient will be eligible for these groundbreaking, life-altering therapies before the disease progresses too far.+1
Medicare Coverage And The Cost Of Innovation
While the clinical milestones are extraordinary, the financial realities of these new treatments are daunting. Monoclonal antibodies for Alzheimer’s carry exorbitant list prices, frequently exceeding $26,000 to $32,000 per year, not including the facility fees for the bi-weekly or monthly IV infusions, the required MRI scans to monitor for brain swelling, and the specialized biomarker testing.
Because Alzheimer’s disease predominantly affects older adults, the financial burden falls heavily on the Centers for Medicare & Medicaid Services (CMS). To balance patient access with systemic affordability, Medicare implemented a Coverage with Evidence Development (CED) pathway. This policy dictates that Medicare will cover these expensive drugs, but only if the prescribing physician enrolls the patient in a national registry to track real-world safety and efficacy data. Even with Medicare coverage, patients are responsible for a 20% coinsurance under Part B, which can equate to thousands of dollars in out-of-pocket costs annually unless offset by a robust supplemental Medigap plan.+2
What This Means For Patients And Caregivers
The evolution of dementia treatment has shifted the narrative from inevitable decline to proactive disease management. However, this new era demands that patients and their families become highly educated healthcare consumers. Accessing the latest therapies requires swift action at the very first signs of cognitive impairment, aggressive advocacy to secure specialized biomarker testing, and a deep understanding of complex insurance rules.
The journey of Alzheimer’s care is no longer a passive experience of symptom management; it is an active, medically intensive process. While the scientific community continues to refine these therapies and explore additional targets like tau proteins, patients today have access to tools that did not exist a decade ago. Navigating the cost and the clinical logistics remains difficult, but for the first time in modern medical history, the trajectory of dementia is finally within the medical community’s power to change.
Dementia Treatment Evolution At A Glance
| Era / Factor | How It Functions | Impact On Patients |
|---|---|---|
| Symptom Management | Oral medications regulate brain chemicals | Offers temporary relief without stopping the underlying disease progression |
| Monoclonal Antibodies | IV infusions physically clear toxic amyloid plaques from the brain | Slows cognitive decline and preserves independence in early-stage patients |
| Biomarker Diagnostics | PET scans and blood tests confirm the exact biological cause of dementia | A strict requirement for both prescribing accuracy and insurance approval |
| Medicare Registries | CMS requires registry enrollment to cover modern Alzheimer’s biologics | Grants access to costly treatments while tracking real-world safety data |
How Early Detection Improves Treatment Outcomes for Serious Illnesses
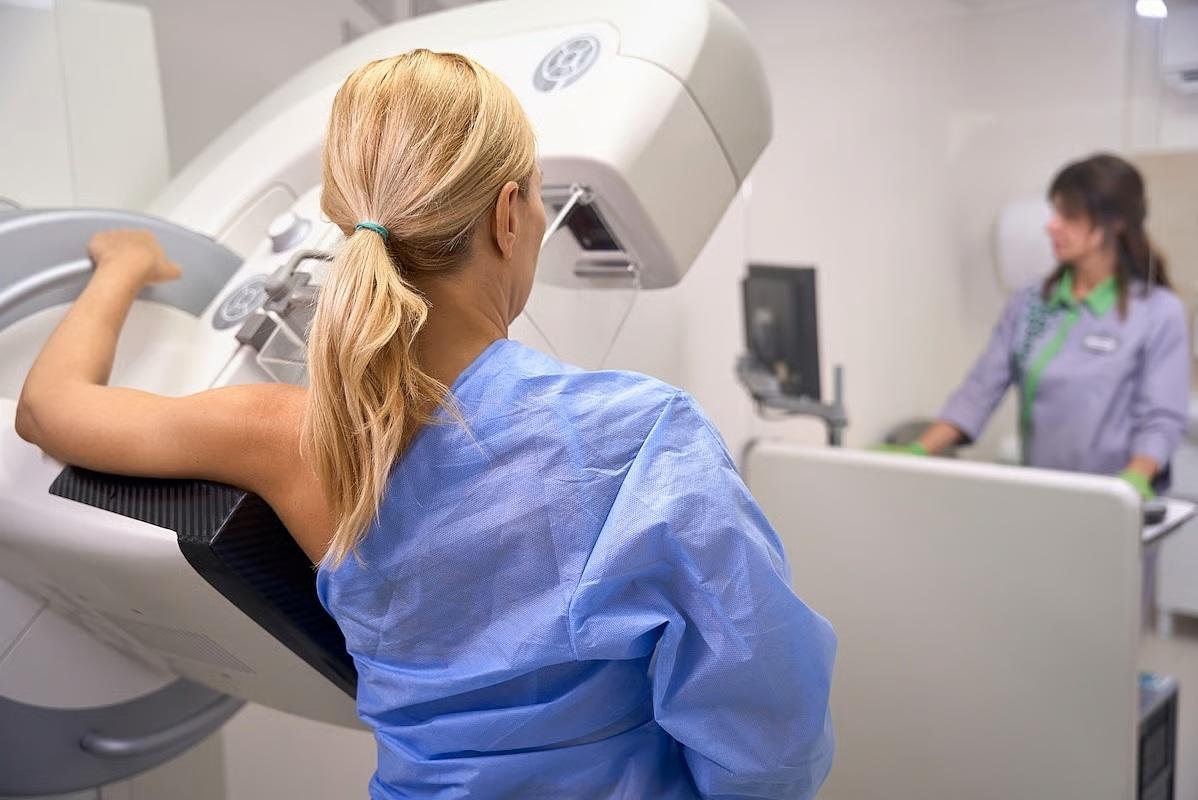
For decades, the American healthcare system has operated on a fundamentally reactive model, waiting for patients to fall visibly ill before deploying expensive, intensive interventions. However, the medical and economic realities of 2026 are forcing a massive shift toward proactive health management. When examining early detection treatment outcomes, the clinical consensus is clear: identifying a severe illness before symptoms manifest is the single most effective way to improve a patient’s long-term survivability.
Beyond the obvious clinical benefits, early detection has become a crucial focal point in the broader conversation about healthcare affordability. Treating advanced-stage chronic conditions or late-stage cancers places an unsustainable financial burden on both the patient and the insurance risk pool. Understanding how preventative screenings alter the trajectory of a diagnosis—and knowing how insurance networks cover these critical tests—is essential for any consumer looking to protect their health and their household budget.
The Clinical And Financial Value Of Preventative Care
When major diseases such as cardiovascular disease, diabetes, or cancer are caught in their earliest stages, the treatment protocols are vastly different than when they are diagnosed late. Early intervention typically requires less aggressive therapies, shorter hospital stays, and lower dosages of specialty medications. This translates directly into significantly higher survival rates and a much faster return to a normal quality of life for the patient.
From a financial perspective, early detection is arguably the most powerful cost-containment tool available in modern medicine. The resources required to manage a localized, early-stage tumor are a fraction of the millions of dollars routinely billed for advanced chemotherapy, complex surgeries, and extended intensive care admissions. By shifting the focus to routine checkups and baseline testing, the healthcare system attempts to circumvent the catastrophic medical claims that drive up annual insurance premiums for everyone.
How Federal Mandates Guarantee Free Screening Access
To encourage widespread participation in preventative healthcare, the Affordable Care Act mandates that most private health insurance plans cover a specific list of evidence-based screenings at no out-of-pocket cost to the patient. This means that if a screening is explicitly recommended by the U.S. Preventive Services Task Force with an “A” or “B” rating, insurance companies cannot charge a copayment, coinsurance, or apply the cost to the patient’s annual deductible.
This federal protection ensures that financial anxiety does not deter patients from scheduling critical baseline exams like mammograms, colonoscopies, and routine blood pressure checks. Even if a patient has not yet met their high deductible for the year, these specific, age-appropriate preventative services must remain entirely free of charge when performed by an in-network provider. However, the strict definitions governing these free services often lead to unexpected medical bills if consumers do not fully understand the coding rules.
Navigating The Hidden Costs Of Diagnostic Follow-Ups
The line between a “preventative” screening and a “diagnostic” procedure is one of the most confusing aspects of medical billing. If a patient goes in for a routine, preventative colonoscopy and the physician finds and removes a suspicious polyp, the insurance coding frequently changes from a preventative service to a diagnostic intervention. Once that diagnostic code is applied, the patient may suddenly be responsible for standard cost-sharing fees, including unexpected facility charges.
Furthermore, if a patient schedules a screening specifically because they are already experiencing symptoms, the visit is legally classified as diagnostic from the very beginning. Patients must be highly proactive when communicating with their doctors and billing departments to ensure they understand exactly how their appointments will be coded. Knowing these nuances is a critical part of effectively using health insurance coverage in 2026 without falling victim to surprise medical debt.
The Rise Of AI And Advanced Genomic Screenings
As we move deeper into 2026, the technology driving early detection is advancing at a staggering pace. Medical providers are increasingly utilizing artificial intelligence algorithms to review routine imaging, catching microscopic abnormalities in lung and breast tissue that human eyes might miss. Simultaneously, the market is seeing a surge in “liquid biopsies”—simple blood tests capable of detecting fragments of cancer DNA long before a traditional tumor physically forms.
While these innovations promise to revolutionize early detection, they are currently at the center of intense coverage battles between hospitals and insurance carriers. Because many of these advanced genomic tests are new, insurers frequently categorize them as experimental and refuse to cover their high out-of-pocket costs. Until these cutting-edge diagnostics are universally adopted into federal preventative guidelines, patients will likely face an uphill battle securing insurance authorizations for the most advanced screening tools available.
What This Means For Your Long-Term Health Strategy
Ultimately, achieving the best possible treatment outcomes requires the patient to act as the chief executive of their own healthcare journey. Waiting for a doctor to suggest a screening is no longer a viable strategy. Patients must educate themselves on their specific family medical history, understand the recommended screening ages for their demographic, and aggressively advocate for those tests during their annual wellness visits.
Health insurance is designed to protect against catastrophic loss, but its greatest value lies in its ability to fund preventative care. By taking full advantage of federally mandated free screenings, understanding the boundaries of diagnostic billing, and staying informed about emerging detection technologies, consumers can dramatically shift the odds in their favor. Early detection is the ultimate convergence of good medicine and smart financial planning.
Early Detection Economics At A Glance
| Market Factor | How It Functions | Impact On Patients |
| Clinical Intervention | Catches diseases before they spread or cause severe symptoms | Results in less aggressive treatments and higher survival rates |
| Federal Mandates | Requires insurers to fully cover specific preventative screenings | Removes upfront cost barriers for routine baseline exams |
| Diagnostic Billing | Shifts billing codes when abnormalities are found or symptoms exist | Can trigger unexpected deductibles and copayments |
| Advanced Screenings | Utilizes AI and DNA blood tests to spot early disease markers | Often requires exhausting insurance appeals due to high costs |
