
Connect with Us


The Future of AI Drug Discovery in Modern Medicine

For decades, bringing a new prescription medication to the consumer market has been a notoriously slow and expensive endeavor. The traditional pharmaceutical pipeline relies heavily on physical trial-and-error, often taking over a decade and billions of dollars to shepherd a single viable compound from a laboratory bench to a pharmacy shelf. However, as we navigate 2026, artificial intelligence is fundamentally dismantling this outdated model. AI-powered drug discovery is no longer a speculative concept; it is an active, driving force reshaping how the medical industry identifies, tests, and manufactures life-saving treatments.
While the scientific community celebrates the rapid acceleration of novel therapies, healthcare economists and insurance experts are watching this evolution through a different lens. The core question for the American consumer is whether the massive financial efficiencies generated by artificial intelligence will actually trickle down to the patient. Understanding how AI changes the pharmaceutical business model is essential for predicting the future of insurance formularies, monthly premiums, and the out-of-pocket cost of modern medicine.
Shrinking The Pharmaceutical Development Timeline
The traditional bottleneck in drug development is the initial discovery phase, where researchers must manually screen thousands of chemical compounds to find one that effectively binds to a specific disease target. Artificial intelligence bypasses this physical limitation by simulating these complex molecular interactions digitally. Advanced machine learning algorithms can analyze massive datasets of biological structures in a matter of days, predicting how different synthetic molecules will behave inside the human body before a single physical prototype is ever synthesized.
By utilizing predictive models to map protein folding and molecular binding, AI eliminates the vast majority of dead-end compounds that historically fail in early-stage clinical trials. This hyper-targeted approach dramatically accelerates the preclinical timeline. For the patient, this means therapies for complex, treatment-resistant conditions—such as aggressive neurodegenerative diseases or rare cancers—can enter human trials years faster than previously possible, offering immediate hope to populations that cannot afford to wait for traditional science to catch up.
The Economics Of Artificial Intelligence In R&D
The financial implications of this accelerated timeline are profound. Historically, the pharmaceutical industry has heavily justified the exorbitant list prices of new medications by pointing to the “sunk costs” of research and development. Because nine out of ten drugs fail during clinical trials, manufacturers argue that the price of the one successful drug must cover the financial losses of the nine failures.
However, AI systematically removes this financial risk. By drastically reducing the number of failed clinical trials and cutting years off the development cycle, artificial intelligence significantly lowers the capital required to bring a drug to market. The critical debate in 2026 is whether the pharmaceutical industry will use these massive R&D savings to lower launch prices for the consumer, or simply absorb them to widen their corporate profit margins. As we continually analyze how pharmaceutical companies influence drug pricing, it is clear that technological efficiency does not automatically guarantee market affordability without aggressive regulatory oversight.
The Impact On Health Insurance Formularies
As AI successfully pushes a higher volume of targeted therapies through the clinical pipeline, health insurance companies are preparing for a massive influx of new, specialized medications hitting the market simultaneously. This surge presents a complex logistical and financial challenge for insurance carriers. Every new drug approved by the FDA drug approval process must be rigorously evaluated by an insurer’s pharmacy and therapeutics committee to determine if it will be covered, at what tier, and under what conditions.
To manage this flood of new therapies, insurers are likely to implement even stricter utilization management tactics. Patients can expect a heavier reliance on prior authorizations and step-therapy protocols as insurance companies attempt to force patients toward older, cheaper generic medications before approving newly minted, AI-discovered brand names. While the science of medicine is accelerating, the administrative friction designed to protect corporate insurance budgets is simultaneously intensifying.
What This Means For The Patient Experience
The integration of artificial intelligence into drug discovery represents one of the most significant medical breakthroughs of the modern era. We are entering an age where bespoke molecules can be rapidly engineered to target the exact genetic profile of a localized disease. Yet, scientific innovation is only as valuable as its accessibility.
For the everyday healthcare consumer, the rise of AI-powered medicine demands heightened advocacy. Patients must actively pressure lawmakers and insurance regulators to ensure that the cost-savings generated by machine learning are reflected at the pharmacy counter, rather than strictly in corporate earnings reports. The future of medicine is faster and smarter, but the ongoing battle for fair, transparent, and affordable healthcare remains entirely in the hands of the educated consumer.
AI Drug Discovery Economics At A Glance
| Market Factor | How It Functions | Impact On Patients |
| Digital Simulation | AI predicts molecular interactions without physical testing | Brings life-saving therapies to clinical trials years faster |
| Reduced R&D Costs | Lowers the rate of failed clinical trials and wasted capital | Weakens the industry’s justification for astronomical launch prices |
| Formulary Congestion | A surge of new drugs hits the commercial market simultaneously | Triggers stricter insurance prior authorizations and network hurdles |
| Precision Targeting | AI engineers highly specific compounds for complex diseases | Improves clinical outcomes while reducing adverse side effects |
How Robotic Surgery Is Changing Modern Medical Procedures
Not long ago, the idea of a robot operating on a human being felt like science fiction. Today, robotic surgery has transitioned from a medical novelty to a fundamental pillar of modern healthcare. Across urology, gynecology, orthopedics, and general surgery, advanced platforms are allowing surgeons to perform highly complex procedures with a level of precision that human hands simply cannot match. As we move deeper into 2026, the adoption of these systems is accelerating rapidly, fundamentally altering the patient experience and the economics of the operating room.
However, this technological revolution brings a unique set of challenges for the American healthcare consumer. While the clinical benefits of smaller incisions and faster recovery times are well-documented, the multi-million-dollar price tags attached to these surgical robots are quietly driving up facility fees. For patients, understanding how robotic surgery works is only half the battle; navigating how health insurance covers these cutting-edge interventions is equally critical.
The Clinical Advantages Of Robotic Assistance
It is important to clarify that surgical robots do not operate autonomously. They are sophisticated, non-autonomous tools strictly controlled by a human surgeon seated at a specialized console. Through high-definition, 3D magnification and highly articulated mechanical arms, these systems filter out natural hand tremors and allow for a greater range of motion than traditional laparoscopic instruments. This allows surgeons to navigate tight anatomical spaces with incredible dexterity.
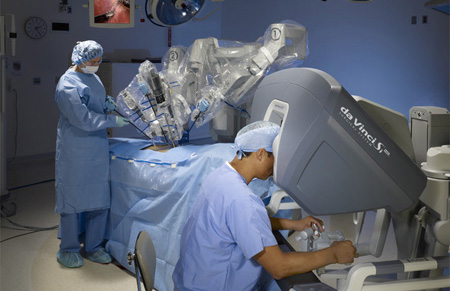
The benefits for the patient are substantial. Because the mechanical arms require significantly smaller incisions than traditional open surgery, patients routinely experience less blood loss, lower infection rates, and reduced postoperative pain. According to data from the American College of Surgeons, these minimally invasive approaches consistently correlate with shorter hospital stays and a faster return to normal daily activities. In specialties like prostatectomies or complex cardiac valve repairs, robotic assistance has rapidly become the preferred standard of care.
The High Cost Of Upgrading The Operating Room
While the clinical outcomes are overwhelmingly positive, the financial barrier to entry is immense. A state-of-the-art robotic surgery system can cost a hospital anywhere from $1.5 million to $2.5 million upfront, not including the expensive, proprietary disposable instruments required for every individual procedure. Furthermore, these machines require costly annual maintenance contracts and rigorous, specialized training programs for the surgical staff.
To recoup these massive capital investments, hospitals must maintain a high volume of robotic procedures. Consequently, healthcare facilities frequently use their robotic capabilities as a major marketing tool to attract patients seeking the latest medical advancements. However, this high overhead is inevitably baked into the hospital’s chargemaster, leading to facility fees that are notably higher than those associated with traditional, non-robotic surgeries.
How Health Insurance Handles Robotic Claims
When a patient undergoes a robotic procedure, the way the hospital bills the insurance company can be a source of significant confusion. Currently, there is rarely a unique insurance billing code specifically designed to trigger higher reimbursement strictly because a robot was used. Instead, insurance companies generally reimburse robotic surgeries at the same rate they would pay for standard laparoscopic procedures, placing the burden of the expensive technology back on the hospital.
Because of this reimbursement gap, some hospitals attempt to balance their ledgers by passing “technology fees” or increased operating room charges directly onto the patient. During standard hospital and insurance negotiations, insurers fight to suppress these extra charges. For the patient, this means that even if a major commercial insurer pre-authorizes the surgery, the higher baseline facility fee will inevitably consume a larger portion of their annual deductible and coinsurance limits.
The Future Of Data-Driven Surgery
Looking ahead, the next frontier of robotic surgery is not just mechanical; it is digital. The newest generation of surgical robots operates as massive data-collection hubs. These machines record thousands of data points during a single procedure, measuring instrument pressure, movement efficiency, and operative time.
By integrating Artificial Intelligence (AI) and machine learning into these systems, developers are creating real-time feedback loops. AI algorithms can overlay 3D preoperative imaging onto the surgeon’s live view, guiding optimal implant placement during joint replacements or helping to identify critical nerve bundles during tumor removals. As these technologies miniaturize, they are also expanding out of major academic hospitals and into smaller, more accessible ambulatory surgical centers.
What This Means For Patient Choices
For the modern healthcare consumer, the rise of robotic surgery requires a more proactive approach to pre-surgical planning. When a physician recommends a robotic procedure, patients should actively question whether the robotic approach offers a statistically significant clinical advantage for their specific condition over a traditional laparoscopic method.
Furthermore, patients must engage deeply with their insurance carriers prior to scheduling the operation. Requesting a detailed estimate of the hospital facility fees, verifying the surgeon’s in-network status, and clarifying how the insurer handles specific robotic equipment charges can prevent a devastating surprise bill. Robotic surgery represents the absolute pinnacle of medical innovation, but ensuring it remains an affordable option requires diligent consumer advocacy.
Robotic Surgery Economics At A Glance
| Market Factor | How It Functions | Impact On Patients |
| Clinical Precision | Surgeons use robotic arms for enhanced dexterity and 3D visualization | Leads to smaller incisions, less pain, and faster recovery times |
| Capital Costs | Hospitals spend millions acquiring and maintaining surgical robots | Drives up overall facility fees and operating room charges |
| Insurance Coding | Often billed under standard laparoscopic procedure codes | Can result in disputed “technology fees” or higher out-of-pocket costs |
| Outpatient Migration | Miniaturized systems are moving into ambulatory surgical centers | May increase local access to advanced care outside of major urban hubs |
How Digital Health Records Are Transforming Patient Care
Electronic health records (EHRs) were initially pitched as a simple digital upgrade. While the reality has been more complex, they are now the backbone of modern healthcare, used by roughly 90% of U.S. office-based clinicians. This widespread adoption matters: digitized patient information can easily follow the patient, support real-time clinical decisions, reduce preventable errors, and seamlessly align multiple providers around a single clinical picture.
Still, the fine print matters. A digital record is not automatically a better record, and an EHR system does not transform care just because a hospital bought one. The benefits depend on how well the system is designed, whether information can actually move between providers, and whether clinicians can use the record without getting buried in documentation burden. That tension is part of what makes digital records so important and so frustrating at the same time. They have real potential to improve care, but only when the technology serves the patient instead of overwhelming the people trying to use it.
Why Digital Health Records Matter More Than Paper Charts
Paper charts were limited in ways that modern healthcare can no longer afford. They were hard to search, difficult to share quickly, vulnerable to missing pages or incomplete histories, and often trapped inside a single office or hospital. Digital records changed that basic equation. CMS explains that an EHR includes core clinical and administrative information such as medications, vital signs, lab data, immunizations, radiology reports, and progress notes, while also supporting decision support, quality management, and outcomes reporting. In other words, the record is no longer just a passive storage system. It can become part of the care process itself.
That shift matters most when care gets complicated. A patient may see a primary care physician, a specialist, a lab, an imaging center, and a hospital within a short span of time. When those settings can access timely and relevant information, care becomes less fragmented. ASTP, the federal office overseeing health IT policy, says EHR systems can improve care coordination by organizing patient information and distributing it among authorized providers, including through alerts that notify clinicians when a patient has been hospitalized and may need follow-up. That is one of the clearest ways digital records transform patient care: not by replacing doctors, but by reducing the gaps between them.
How EHRs Improve Safety And Clinical Decisions
One of the strongest arguments for digital health records is patient safety. When records are electronic, clinicians can review medication lists more quickly, check allergy information, see test results without waiting for a faxed chart, and use built-in decision support tools that flag possible medication interactions or missing preventive care. CMS says EHRs have the potential to streamline workflows and support evidence-based decision support directly within care delivery. AHRQ’s patient safety resources also note that technology can increase standardization, improve efficiency, and reduce some types of errors when implemented well.
This is especially important in diagnosis and follow-up. ASTP says EHRs can improve diagnostics and patient outcomes by helping providers identify eligible patients for preventive measures, track patients with specific conditions, and review medication use across a population. That population-level view is something paper records did very poorly. A provider can now search across patient panels, identify people overdue for screenings, or flag trends that suggest a higher-risk group may need outreach. In practice, that can mean earlier intervention, more consistent monitoring, and fewer patients falling through the cracks.
How Digital Records Change The Patient Experience
The transformation is not limited to clinicians. Patients increasingly expect their health information to be available electronically, whether they need test results, visit summaries, refill requests, or records shared with a new doctor. ASTP says EHRs can increase patient participation in care by helping providers communicate more effectively and involve patients more directly in treatment decisions. A recent systematic review also found a positive relationship between patient access to electronic health records and stronger healthcare engagement, including treatment adherence, self-management, satisfaction, and communication.
That matters because better patient care is not only about what happens in an exam room. It is also about whether patients can understand their care plan, follow instructions, review their medications, and catch mistakes before those mistakes become harmful. A digital record or patient portal cannot solve every problem, but it can make the patient less dependent on memory, paper handouts, or repeated phone calls to piece together what happened during a visit. This is part of the same broader technology shift affecting other parts of care, including the growing use of wearable health devices and remote monitoring tools that produce data clinicians increasingly need to organize and interpret.
Where Interoperability Still Changes Everything
If there is one word that defines the promise and the frustration of digital records, it is interoperability. The real value of an EHR is not just that data is digital. It is that the data can move securely and meaningfully between authorized users. ASTP says health IT interoperability enables the secure and seamless exchange of electronic health data, while CMS has repeatedly emphasized patient access and data sharing through its interoperability policies. That is a policy issue, but it is also a bedside issue. A record that cannot follow the patient still leaves major holes in care.
The practical effect is easy to see. When interoperability works, a hospital discharge summary can reach a primary care doctor faster, medication lists can be reconciled more accurately, and duplicate testing may be reduced. When interoperability fails, patients often become the ones carrying the burden, repeating their histories, moving lab results between offices, and hoping nothing important gets lost in transit. That is why digital records are transforming care, but not evenly. Their value rises when systems talk to each other and falls when data stays locked inside institutional silos.
What Digital Health Records Improve Most
The gains from EHRs are easier to understand when broken into specific care functions rather than treated like one giant promise.
| Area of Care | How Digital Records Help | Why It Matters for Patients |
|---|---|---|
| Medication Safety | Tracks medications, allergies, and interactions | Helps reduce avoidable prescribing mistakes |
| Care Coordination | Shares records among authorized providers | Reduces fragmented care across offices and hospitals |
| Preventive Care | Identifies gaps in screenings and follow-up | Supports earlier intervention and routine care |
| Patient Access | Makes summaries and results easier to retrieve | Helps patients stay engaged in treatment |
| Population Health | Lets providers review trends across patient groups | Improves outreach for higher-risk patients |
This is where the strongest case for digital records lives. They are not magical, but they can support safer prescribing, more organized follow-up, and better continuity of care. Federal health IT guidance repeatedly points to these same functions: improved quality, stronger coordination, and easier access to relevant health information for both providers and patients.
The Burdens And Risks That Get Less Attention
The optimistic version of the EHR story often leaves out the burden on clinicians. AHRQ and PSNet materials make clear that digital systems can improve safety and standardization, but poor design or poor implementation can also increase workload, documentation burden, and workflow disruption. A systematic review summarized by PSNet found that EHRs reduced documentation time for nurses but often increased it for physicians, with usability and workstation design playing a major role. That is a reminder that digital transformation can improve patient care while simultaneously straining the workforce delivering it.
There are also concerns about information overload and data quality. Research in the medical literature has warned that EHR-related information overload can create patient safety issues, while other studies point to documentation errors, data heterogeneity, and integrity problems that can affect how records are interpreted. A digital chart can centralize information, but if that information is cluttered, duplicated, biased, or inaccurate, the system may create new risks even as it solves old ones. This is one reason the public should be cautious about the simplistic assumption that digital always means better. Better systems usually come from better design, governance, and clinical workflow, not from digitization alone.
What This Means For The Future Of Patient Care
Digital health records have already changed patient care, and they will keep doing so because modern medicine increasingly depends on connected information. From prescription safety to chronic disease follow-up to hospital discharge coordination, EHRs now shape how care is documented, shared, measured, and improved. ASTP and CMS both frame digital records as a foundation for better coordination, better patient access, and more efficient care delivery. That foundation is real.
But the more honest conclusion is that digital health records are transforming care in two directions at once. They are making it easier to connect data, support decisions, and involve patients more directly in their treatment. At the same time, they are exposing the limits of bad usability, weak interoperability, and excessive documentation demands. The technology has moved healthcare beyond paper. The next challenge is making sure it also moves healthcare toward systems that are clearer, safer, and easier for both patients and clinicians to navigate. For readers who want the official federal overview of how EHRs improve quality and coordination, ASTP’s guidance on electronic health records is one of the best starting points.
The Rise of Wearable Health Devices — And How Doctors Use the Data
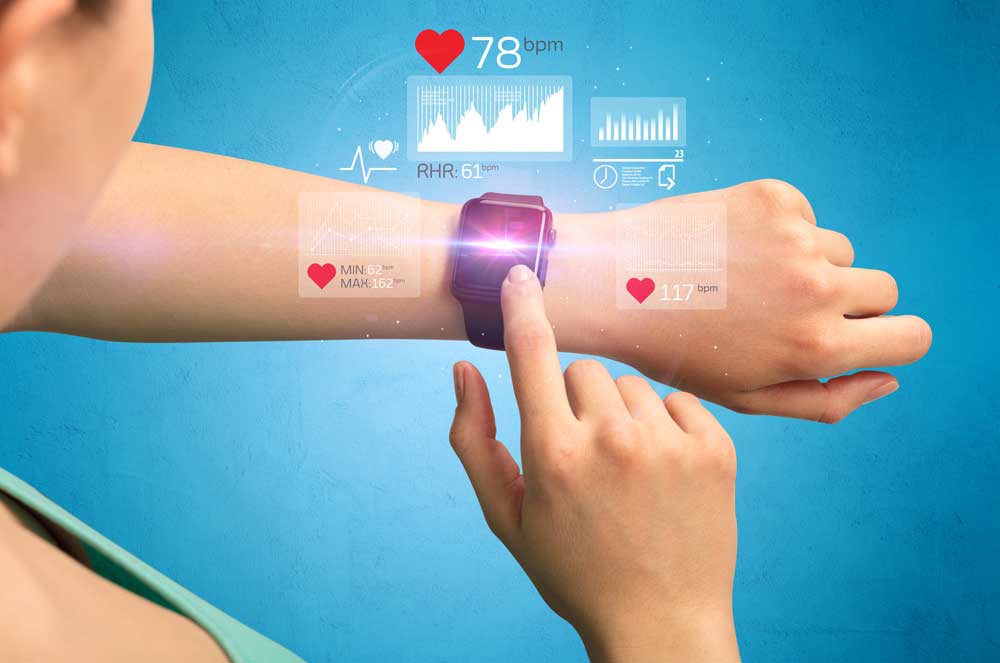
Walk into almost any gym, office, airport, or grocery store, and you will see people wearing some form of health tech on their wrists, fingers, or clothing. Smartwatches count steps, rings estimate sleep quality, patches track heart rhythms, and connected glucose monitors send readings in near real time. What started as a fitness trend is now becoming part of the broader healthcare system, as doctors and care teams increasingly look at wearable data to monitor patients between office visits. The shift has been accelerated by remote patient monitoring programs and by growing interest in tools that can capture health trends outside the traditional clinic setting.
That does not mean every graph on a smartwatch is suddenly a medical diagnosis. This is where the conversation often gets oversimplified. Wearables can produce useful information, but doctors do not treat every consumer metric the same way. In practice, clinicians tend to focus on data that is clinically relevant, consistent over time, and tied to a specific care plan. The real story is not that wearable devices are replacing physicians. It is that they are giving physicians a wider view of what may be happening between appointments, especially for patients managing chronic conditions such as hypertension, diabetes, heart disease, or recovery after hospitalization.
Why Wearable Health Devices Are Expanding So Quickly
The appeal of wearable technology is easy to understand. Traditional healthcare often depends on brief snapshots. A patient comes in, gets a blood pressure reading, describes symptoms, and goes home. But many health issues do not behave neatly during a 15-minute office visit. Blood pressure can fluctuate, heart rhythm changes can come and go, glucose levels move throughout the day, and symptoms such as fatigue or poor sleep may be difficult to capture during a single encounter. Wearables help fill some of those gaps by collecting repeated measurements over time. NIH notes that next-generation wearables are being developed to monitor a growing range of health indicators in partnership with healthcare providers, not just for personal fitness use.
Another reason for the growth is that the healthcare system has become more comfortable with remote patient monitoring as a care model. CMS defines remote patient monitoring as the collection of a patient’s health data through a connected medical device that transmits information to a provider, who can then use that data to manage the patient’s condition. That framework matters because it shows how wearable and connected devices are moving from the wellness category into structured medical care for certain patients.
The FDA is also paying closer attention to this space. Its digital health resources and device listings show that sensor-based digital health technologies now include wearable forms such as smartwatches, rings, bands, and patches. In other words, this is no longer a niche corner of consumer electronics. It is an active part of digital medicine, with growing regulatory interest and expanding clinical use.
What Types of Data These Devices Collect
Not all wearable data is equally useful in a medical setting. Some devices are designed mainly for wellness tracking, while others are cleared or authorized for specific healthcare applications. Doctors are generally most interested in data that helps them understand trends, flag deterioration, or guide treatment decisions. Common examples include heart rate, heart rhythm, blood pressure, blood glucose, oxygen saturation, weight changes, physical activity, and sleep-related patterns. CMS specifically points to readings such as blood pressure, weight, and glucose as examples of data collected through connected medical devices for remote monitoring.
Here is a simple breakdown of how that data can matter in practice:
| Device Type | Common Data Collected | How Doctors May Use It |
|---|---|---|
| Smartwatch or heart monitor | Heart rate, rhythm alerts, activity levels | Spot trends, review possible arrhythmia events, monitor recovery progress |
| Continuous glucose monitor | Glucose readings throughout the day | Adjust diabetes treatment and identify dangerous highs or lows |
| Connected blood pressure cuff | Blood pressure trends over time | Evaluate hypertension control outside the clinic |
| Pulse oximeter or respiratory monitor | Oxygen saturation, pulse | Track respiratory status in selected patients |
| Smart scale | Weight fluctuations | Monitor fluid retention and heart failure risk |
This is where wearables become more than gadgets. Repeated data points can sometimes reveal patterns that a single office visit would miss. For patients with chronic disease, that can give care teams a chance to intervene earlier rather than waiting for a problem to worsen. The AMA’s remote monitoring guidance highlights that RPM data can support better conversations between patients and physicians and help teams respond more quickly when conditions begin to decline.
How Doctors Actually Use Wearable Data
In real-world care, doctors rarely use wearable data in isolation. They use it as one piece of a larger clinical picture that includes symptoms, physical exams, medical history, medication use, lab work, and imaging when needed. The most useful wearable data is often trend data. A physician may not react to one odd reading, but a week or month of consistent patterns can be far more meaningful.
For example, a cardiologist may review rhythm notifications or extended heart-rate patterns when evaluating palpitations. A primary care doctor may look at home blood pressure readings to determine whether a medication is working outside the stress of an office setting. An endocrinologist may rely on continuous glucose monitoring trends to decide whether insulin timing or dosage needs to change. In hospital-at-home or post-discharge settings, care teams may track weight gain, oxygen levels, or activity levels as early warning signs that a patient needs attention. NIH and CMS both point to these kinds of wearable and connected monitoring uses as part of the broader move toward more continuous care.
Doctors also use the data to improve conversations. Patients often say they feel “off,” “tired,” or “short of breath,” but those descriptions can be hard to measure. Wearable trends sometimes give those symptoms more context. If sleep patterns worsen, activity levels decline, blood pressure rises, or glucose swings become more extreme, that information can help a physician ask better questions and tailor follow-up care more effectively. That is one reason why digital monitoring has become part of a broader shift toward more personalized and preventive healthcare.

Where Wearables Help Most In Treatment
Wearables tend to be most useful when they are tied to a defined clinical problem. They are particularly relevant in chronic disease management, recovery tracking, and situations where frequent office visits are impractical. The strongest value often comes when the device is connected to a care team that knows what metrics matter and what action should follow. That is also why patients researching broader treatment coverage may find it helpful to review how insurers and care teams handle monitoring and follow-up through the site’s own treatment coverage content.
Chronic disease management is one of the clearest examples. For diabetes, continuous glucose monitors can show how food, medication, stress, and activity affect glucose throughout the day. For hypertension, home and connected blood pressure readings may show whether blood pressure control looks very different at home than it does in a clinic. For heart failure or respiratory conditions, connected devices may help care teams detect changes before they become emergencies. A growing body of research has linked remote monitoring programs with improvements in adherence, earlier intervention, and in some cases better quality-of-life outcomes, though the impact varies by patient population and program design.
The Limits Patients Should Understand
This is the part many glowing headlines skip. Not every wearable metric is medical-grade, and not every alert means something is wrong. Consumer devices can be helpful, but they can also create anxiety, generate false positives, or produce readings that need professional interpretation. Even when devices are accurate, raw numbers do not explain the whole clinical story. A slightly elevated heart rate could reflect exercise, stress, dehydration, illness, or medication effects. A sleep score may be interesting, but it is not the same thing as a formal sleep evaluation.
There are also practical issues around workflow. Doctors and health systems cannot realistically review endless streams of unfiltered data for every patient. That is why successful remote monitoring programs usually define in advance which metrics are being tracked, how often data is reviewed, and what thresholds should trigger follow-up. The CMS and HHS guidance around remote monitoring reflects that this is a structured clinical service, not simply a patient emailing screenshots from a smartwatch. For readers who want the official federal framework, HHS provides a useful overview of remote patient monitoring.
Privacy and cybersecurity remain another concern. Connected monitoring devices can involve sensitive health data moving across apps, networks, and provider systems. The FDA has warned about cybersecurity vulnerabilities in certain patient monitors, underscoring that digital convenience can also create new risks if devices or connected systems are not properly secured.
What This Means For Patients And Doctors
The rise of wearable health devices is not just a consumer tech story. It is part of a deeper shift in how healthcare is delivered. Instead of relying only on occasional snapshots, doctors can increasingly see longitudinal patterns that may reveal how a patient is actually doing in daily life. That can be valuable for treatment decisions, medication adjustments, and earlier intervention. But the benefit depends on context, data quality, and whether the information is tied to a real care plan.
For patients, the smartest approach is to see wearables as tools, not verdicts. The best devices can help people become more engaged with their health and give doctors better information than they once had. But they are most useful when their data is interpreted carefully, used consistently, and connected to professional medical judgment. The devices may be getting smaller and smarter, but the fine print still matters. Not every number needs panic. Not every graph changes treatment. The real value comes when wearable data helps turn scattered health signals into better care.
Pharmacy Apps, Price Transparency Tools, and Drug Cost Tracking
Disclosure: America’s Fair Healthcare provides educational information only and does not offer medical, legal, or insurance advice. Drug prices and coverage rules vary by plan, pharmacy, state, and eligibility. Always confirm final pricing with your pharmacy and your health plan.
Prescription drugs are one of the most common places people get blindsided by “real-world” healthcare costs. The problem isn’t just that medications can be expensive. It’s that the price can change based on the pharmacy you choose, whether you run it through insurance, whether the drug is on your plan’s formulary, and whether a coupon or discount program is treated as cash instead of a claim.
That’s where pharmacy apps and price transparency tools come in. Used the right way, they can help you compare prices, find lower-cost options, and track your monthly spend. Used the wrong way, they can create confusion, delays, and a nasty surprise when you realize your purchase didn’t count toward your deductible or out-of-pocket maximum.
This guide explains what these tools do, how to use them safely in 2026, and how to track drug costs like a pro. If you’re dealing with restrictions like prior authorization or step therapy, start here as well: Prescription Drug Coverage & Prior Authorization.
Why Drug Prices Feel Random (Even When You “Have Insurance”)
Most people assume a prescription has one price. In reality, there are often several possible prices for the same medication:
The “cash price” is what the pharmacy charges if you don’t use insurance. The “insurance price” is based on your plan’s negotiated rate and your copay or coinsurance. Discount programs can produce another price, sometimes lower than insurance, but with different tradeoffs.
Even within insurance, the final cost can change depending on your deductible status, whether the drug is a preferred formulary option, and whether your plan requires special steps before it will pay. That’s why drug costs are a major part of the “real monthly cost” conversation we cover here: Premiums, Subsidies, and the “Real” Monthly Cost in 2026.
What Pharmacy Apps Actually Do
Pharmacy apps usually fall into three buckets: pharmacy-owned apps, discount-price apps, and plan/insurer apps.
Pharmacy-owned apps help you manage refills, set reminders, transfer prescriptions, and sometimes show estimates based on your insurance. They’re helpful for organization and refill timing, especially if you manage multiple medications.
Discount-price apps focus on price comparison. They may show different prices at different pharmacies, offer digital coupons, and sometimes highlight lower-cost alternatives. These tools can be valuable, but you need to understand whether the discount is treated as a cash purchase or an insurance claim.
Plan/insurer apps often provide formulary lookups, preferred pharmacy lists, and mail-order options. These are useful because they reflect your plan’s specific rules, including tiers, prior authorization, and step therapy requirements.
Price Transparency Tools: What They Help With (and What They Don’t)
Price transparency tools can be great for answering a simple question: “Where is this medication cheaper today?” For many common prescriptions, prices can vary widely between pharmacies even within the same ZIP code.
But these tools have limits. Some show pricing that doesn’t reflect your exact insurance plan. Some show a price that applies only if you use a specific discount program. Others may not capture specialty pharmacy requirements or plan restrictions that affect whether you can actually fill the prescription at that location.
The best way to use transparency tools is to treat them as a starting point, then verify the final price at the pharmacy counter or through your plan’s official channels.
Drug Cost Tracking: The Habit That Prevents “Surprise Months”
Drug cost tracking sounds boring until you experience a month where your routine prescription suddenly doubles in price. Tracking gives you a baseline, so you notice changes quickly and can react while you still have options.
In 2026, drug cost tracking matters for three big reasons. First, formularies and tiers can change year to year. Second, your deductible resets annually for most plans, which can make January feel more expensive. Third, prior authorization or step therapy changes can delay refills, forcing last-minute out-of-pocket spending.
A simple tracking approach is to record the medication name, dose, pharmacy, whether you used insurance or cash, and what you paid. Over time, you’ll see patterns: which pharmacies are consistently cheaper, which months are higher-cost, and which drugs are the biggest drivers of your spending.
The Big “Gotcha”: Discounts vs Insurance Claims
Here’s the most important rule: if you buy a medication using a discount price that is treated as a cash transaction, it may not count toward your deductible or your out-of-pocket maximum.
That doesn’t mean discount programs are bad. It means you should choose them intentionally. If your plan has a high deductible and you’re early in the year, a discount could save money immediately. But if you are trying to reach your deductible or out-of-pocket maximum because you have ongoing care needs, insurance-processed claims may matter more.
If you’re unsure, ask the pharmacy this specific question: “Will this run through my insurance as a claim, or will it be treated as cash?” That one sentence can prevent a lot of confusion later.
Mail Order and 90-Day Fills: Quiet Ways to Lower Costs
Many plans encourage mail-order prescriptions or 90-day supplies for maintenance medications. Sometimes the cost is lower; sometimes the convenience is the bigger benefit. Either way, if you take long-term medications, it’s worth checking.
Mail order isn’t always best for every medication. Some people prefer local pickup for timing, temperature-sensitive drugs, or faster changes when a prescription is adjusted. But for stable long-term prescriptions, a 90-day option can reduce both hassle and cost variability.
How to Use These Tools Safely in 2026
A safe, practical workflow looks like this.
First, check your plan’s formulary to confirm the drug is covered and whether restrictions apply. If you see prior authorization or step therapy language, use this explainer: Prescription Drug Coverage & Prior Authorization.
Second, use a price transparency tool to compare pharmacies in your area. Look for major price differences and identify the best options.
Third, call the pharmacy you’re considering and confirm the final price under your insurance. If the discount price is lower, ask whether it will be treated as cash or can be submitted as a claim.
Fourth, track your costs monthly so you can spot changes early.
If you’re shopping for coverage during enrollment and drug costs are a major concern, build your plan choice around medications, not just premiums. This cost lens matters even more in 2026: Premiums, Subsidies, and the “Real” Monthly Cost.
Where to Verify Official Coverage Information
If you’re using Marketplace coverage, start with official enrollment and plan information at HealthCare.gov. If you’re reviewing Medicare drug coverage options, the official Medicare site is the right place to confirm plan details: Medicare.gov.
For employer coverage and reimbursement arrangements, confirm the rules in your plan documents and with your benefits team. If you’re navigating HRAs or ICHRA choices, this page can help you frame the switching and timing issues: Employer Options (HRAs/ICHRA) and Plan Switching.
Bottom Line
Pharmacy apps and transparency tools can be powerful, especially when drug costs are driving your monthly budget. The key is using them with a clear goal: compare prices, verify coverage restrictions, and track spending over time.
In 2026, the smartest approach is not choosing one tool and trusting it blindly. It’s combining tools: your plan’s formulary resources for accuracy, transparency tools for comparison, and your own tracking for control. That’s how you keep drug costs from becoming the surprise line item that wrecks your “real monthly cost” plan.
For more coverage, explore Treatment, Affordability, and Resources.
AI Health Insurance Assistants: What They Do, What Can Go Wrong, and How to Protect Patients
Health insurance is already complicated on a good day. Now add a new “helper” into the mix: AI-powered insurance assistants. These tools show up as chatbots on insurer websites, automated phone agents, claim-status bots, prior-authorization (prior auth) workflow assistants, and internal staff copilots that summarize policy rules or draft denial letters.
Used responsibly, AI assistants can speed up basic tasks, reduce paperwork, and help members find answers faster. Used carelessly, they can amplify bias, misstate benefits, leak sensitive information, or turn “efficiency” into a denial machine. Regulators are paying attention, and patients (and clinicians) should too. CMS has clarified that Medicare Advantage plans may use algorithms and AI to assist coverage determinations—but they can’t use predictive tools to override medical necessity or ignore an individual patient’s circumstances.
What is an “AI health insurance assistant”?
An AI health insurance assistant is software that uses automation—often including machine learning or generative AI—to interact with members or support insurer staff. In plain English: it’s a system designed to answer questions, route requests, or recommend decisions at scale.
Common examples include:
Member-service chatbots that explain benefits, find in-network providers, or estimate out-of-pocket costs; claim and billing assistants that track status, flag missing documentation, or generate member messages; prior-auth intake assistants that collect clinical information and route it for review; and internal staff copilots that summarize policy criteria or draft letters.
Where AI assistants can genuinely help patients
When insurers deploy AI with strong guardrails, patients can see real improvements:
Faster answers for routine questions
Most member questions are repetitive: “Is this covered?” “Do I need a referral?” “What’s my deductible?” AI assistants can reduce call wait times and help members navigate plan documents—especially after hours.
Cleaner prior authorization workflows
Prior auth is a notorious bottleneck. CMS has pushed for modernization and interoperability so that payers and providers can exchange information more efficiently, including via standardized APIs. If AI is used to collect complete documentation up front (rather than to “auto-deny”), it can reduce back-and-forth and speed legitimate approvals.
Clearer cost transparency
With U.S. health spending still extremely high, patients need straightforward explanations of what they’ll owe and why. AI assistants can guide members to the right cost tools, help interpret EOBs, and point out when a bill doesn’t match plan rules.
The big risks: denial engines, bad advice, and privacy leaks
Here’s the hard truth: an “assistant” can quietly become a gatekeeper. The risks tend to fall into three buckets—fairness, accuracy, and privacy.
1) Fairness and discrimination at scale
AI can replicate bias faster than humans because it standardizes decisions across millions of encounters. The U.S. Department of Health and Human Services (HHS) Office for Civil Rights has emphasized that nondiscrimination protections apply to the use of AI and emerging technologies in covered health programs and activities, and that organizations should take reasonable steps to identify and mitigate discrimination risks.
2) “Confidently wrong” benefit explanations
Generative AI tools are known for producing plausible-sounding answers that can be incorrect. In an insurance setting, a wrong answer isn’t just embarrassing—it can delay care, mislead a family about costs, or push someone to skip treatment.
This is especially dangerous when a chatbot is treated like an “official policy interpreter,” even though the legally controlling documents are the plan contract and applicable regulations.
3) Prior authorization shortcuts that violate the rules
CMS has been explicit: algorithms or software tools may assist Medicare Advantage plans, but responsibility remains with the plan to ensure compliance. In the CMS FAQ memo, the agency gives an example where an algorithm can predict a length of stay, but that prediction alone cannot be used to terminate post-acute services.
4) Privacy and data security problems
Insurance assistants often touch sensitive information: diagnoses, medications, claims history, and family details. If a chatbot vendor stores transcripts improperly, if tracking tech leaks data from a benefits page, or if employees paste member details into the wrong tool, the harm is immediate.
Even outside insurance, public concern is rising about what happens when people upload medical data into AI tools and whether protections truly match the sensitivity of the information. And from a consumer-protection angle, the FTC has warned about AI-related risks and potential consumer harm, including privacy and security concerns.
What regulators expect from insurers using AI
Two major guideposts matter for insurance AI governance right now: CMS rules for coverage determinations (especially in Medicare Advantage) and state insurance regulator expectations (often influenced by NAIC).
CMS: AI can “assist,” but it can’t replace individualized medical necessity
The CMS memo (Feb. 6, 2024) is one of the clearest statements patients and clinicians can cite when AI-driven utilization management becomes a barrier. The message is simple: tools can support workflows, but they can’t short-circuit the legal standards.
State insurance regulators: governance, oversight, documentation
The NAIC “Model Bulletin: Use of Artificial Intelligence Systems by Insurers” lays out principles-based expectations—fairness, accountability, compliance, transparency, and secure systems—plus the kinds of documentation regulators may request. Many states have moved toward implementing this model bulletin in some form.
A patient-focused checklist: how to use insurer AI tools without getting burned
If you (or a loved one) use an insurer chatbot or automated assistant, treat it like a helpful receptionist—not a final authority.
Ask for the source
When the assistant says something important (“That’s not covered” or “No prior auth needed”), ask it to cite the plan document section, medical policy, or member handbook language. If it can’t, assume it may be wrong.
Get a reference number and save transcripts
Always request a case ID, chat transcript, or confirmation email. If you later appeal a denial, contemporaneous notes matter.
Escalate quickly for anything involving care delays
If the issue involves ongoing treatment, post-acute care, a medication you’re already stable on, or discharge planning, move to a human representative and ask for supervisor review. If you’re in Medicare Advantage and the denial seems driven by a “prediction,” reference CMS’s guidance that predictive tools can’t be the sole basis to terminate services.
Limit what you share
Only provide what’s necessary to route your request. Avoid uploading full medical records into chat tools unless you clearly understand how the information is stored, used, and protected.
What “good” AI insurance assistance should look like
If insurers want AI assistants to build trust instead of backlash, the standard should be higher than “it reduces call volume.” A patient-first assistant should:
Clearly disclose when you’re talking to AI; separate education from decision-making; provide document citations; default to human review when clinical judgment is involved; log every automated recommendation for audit; test for bias across protected classes; and provide an easy path to appeal, including a human explanation written in plain language.
That isn’t just best practice—it aligns with where policy is going. Between CMS guidance on coverage determinations and the NAIC-style governance expectations, “black box” decisioning is getting harder to defend.
Bottom line
AI health insurance assistants are here, and they’re not going away. The fight is about how they’re used. If these tools stay in the lane of navigation and paperwork—helping members find answers, submit complete requests, and understand costs—they can reduce friction. If they drift into automated denial logic, biased decision support, or sloppy data handling, they become a new layer of insurer abuse dressed up as “innovation.”
